
Personalized Skin Cancer Care in Little Rock
What Causes Skin Cancer?
What Are the Different Types of Skin Cancer?
What Does Skin Cancer Look Like?
How is Skin Cancer Treated?
Skin cancer is caused by the abnormal growth of cells in the skin. The most common types include basal cell carcinoma, squamous cell carcinoma, and melanoma. When detected and treated early, many skin cancers can be successfully treated, while delayed treatment can allow some cancers to grow into surrounding tissue or spread to other parts of the body. For patients seeking diagnosis and treatment of skin cancer in Little Rock and throughout Central Arkansas, a full-body skin exam at Dermatology Group of Arkansas can help identify skin cancer and determine appropriate treatment options. Regular skin checks, professional skin exams, and prompt evaluation of suspicious changes remain important for 2026, 2027, and beyond.
The earlier skin cancer is detected, the more treatment options may be available. Patients should monitor their skin for new or changing spots and schedule routine examinations with a dermatologist. As skin cancer diagnosis and treatment continue to evolve, ongoing dermatologic care can help patients address suspicious changes promptly and understand their treatment options now and in the future.
Contact Us Today
Schedule a consultation with Dermatology Group of Arkansas to discuss skin cancer diagnosis and treatment in Little Rock, Central Arkansas, and surrounding areas. Call us at the Dermatology Group of Arkansas at 501-227-8422 or submit a contact form to request a consultation.

Skin Cancer at a Glance
- What is skin cancer?
- What causes skin cancer?
- What are the main types?
- What are common signs?
- How is skin cancer diagnosed?
- How is skin cancer treated?
- Can skin cancer be prevented?
- Why is early detection important?
- Skin cancer is the abnormal growth of cells in skin tissue.
- Most skin cancers are linked to intense or cumulative UV exposure from sunlight, tanning beds, or sun lamps.
- The three main types are basal cell carcinoma (BCC), squamous cell carcinoma (SCC), and melanoma.
- New or changing moles, changes in size, shape, or color, unusual growths, pearly or waxy bumps, bleeding, or sores that do not heal can be warning signs.
- A suspicious lesion may be biopsied and examined under a microscope to confirm whether skin cancer is present and identify its type.
- Treatment depends on the type of skin cancer and may include surgical removal, Mohs surgery, destruction of the cancer, topical creams, radiation, or other treatments.
- Sun protection, avoiding intentional UV exposure, wearing protective clothing, and using broad-spectrum SPF 30 or higher sunscreen can help reduce risk.
- Finding and treating skin cancer early can improve the chances of successful treatment.
Skin Cancer at a Glance
What is skin cancer?
Skin cancer is the abnormal growth of cells in skin tissue.
What causes skin cancer?
Most skin cancers are linked to intense or cumulative UV exposure from sunlight, tanning beds, or sun lamps.
What are the main types?
The three main types are basal cell carcinoma (BCC), squamous cell carcinoma (SCC), and melanoma.
What are common signs?
New or changing moles, changes in size, shape, or color, unusual growths, pearly or waxy bumps, bleeding, or sores that do not heal can be warning signs.
How is skin cancer diagnosed?
A suspicious lesion may be biopsied and examined under a microscope to confirm whether skin cancer is present and identify its type.
How is skin cancer treated?
Treatment depends on the type of skin cancer and may include surgical removal, Mohs surgery, destruction of the cancer, topical creams, radiation, or other treatments.
Can skin cancer be prevented?
Sun protection, avoiding intentional UV exposure, wearing protective clothing, and using broad-spectrum SPF 30 or higher sunscreen can help reduce risk.
Why is early detection important?
Finding and treating skin cancer early can improve the chances of successful treatment.
What Causes Skin Cancer?
Skin cancer develops when abnormal skin cells grow and divide uncontrollably instead of following the body’s normal cell growth and replacement cycle. These abnormal cells can form a tumor and, in some types of skin cancer, invade nearby tissue or spread to other parts of the body.
The most significant risk factor for many skin cancers is exposure to ultraviolet (UV) radiation. UV exposure can come from sunlight or artificial sources such as tanning beds and sun lamps. Both intense, intermittent exposure that causes sunburn—especially blistering sunburns—and cumulative UV exposure over time can increase the risk of developing skin cancer.
Genetics can also play a role. A person’s risk may be influenced by inherited characteristics, family history, skin type, and other factors. However, skin cancer can develop in people without a known family history or other obvious risk factors.
What Are the Different Types of Skin Cancer?
The skin is your body’s largest organ, and it consists of several layers, including the epidermis (the upper or outer layer of skin) and the dermis (the lower or inner layer). The epidermis contains three types of cells: squamous cells, basal cells, and melanocytes. Cutaneous cancer can develop in all three types of cells.
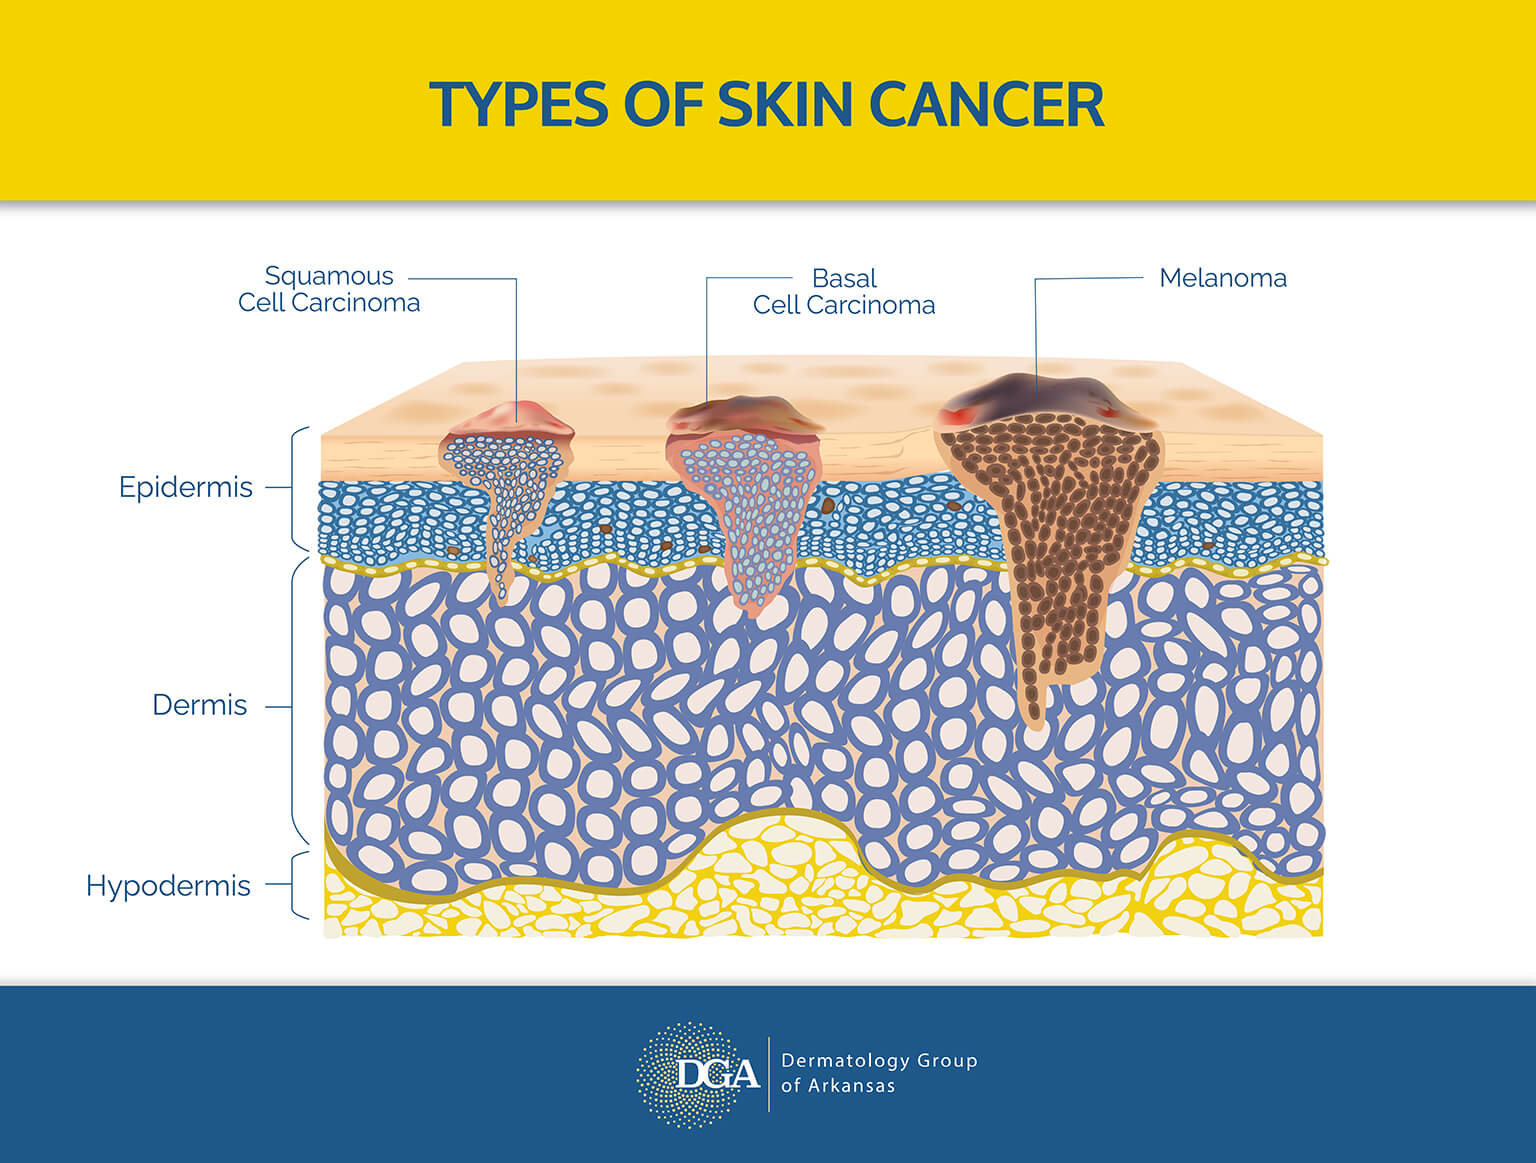
To find the most effective skin cancer treatment from the Little Rock area’s Dermatology Group of Arkansas, we will need to identify the type of skin cancer you have. This is determined by where the cancer originates. The three main types are basal cell carcinoma, squamous cell carcinoma, and melanoma. Basal cell carcinoma begins in your basal cells in the lower part of the epidermis while squamous cell carcinoma occurs in the squamous cells in the upper epidermis, and melanoma starts in the melanocytes – the cells that produce skin pigmentation.
What Is Basal Cell Carcinoma?
Basal cell carcinoma (BCC) is the most common type of skin cancer. It is usually slow-growing and is strongly associated with cumulative sun exposure. BCC rarely spreads to other parts of the body, but it can grow into and damage nearby tissue when left untreated.
BCC skin cancer can be particularly destructive when it develops on areas such as the nose, ears, or around the eyes. On other parts of the body, an untreated BCC can grow deeper into the skin and potentially reach muscle or bone. Early diagnosis and appropriate treatment can help prevent this type of local tissue damage.
What Is Squamous Cell Carcinoma?
Squamous cell carcinoma (SCC) is the second most common type of skin cancer and can be more aggressive than BCC. SCC often grows more quickly and can cause significant local tissue damage if it is not treated.
Unlike BCC, SCC can spread to nearby lymph nodes or other parts of the body, although most SCCs remain confined to the skin. The risk of spread can be higher for SCCs affecting areas such as the lips, ears, hands, and fingers, as well as in people with weakened immune systems. Early diagnosis and treatment can reduce the risk of complications.
What Is Melanoma?
Melanoma is a type of skin cancer that develops from melanocytes, the pigment-producing cells in the skin. Although melanoma can be life-threatening if it spreads, it is often highly treatable when detected and treated early.
Skin Cancer Types Compared
| Basal Cell Carcinoma (BCC) | Squamous Cell Carcinoma (SCC) | Melanoma | |
|---|---|---|---|
| Where it starts | Basal cells in the lower part of the epidermis | Squamous cells in the upper epidermis | Melanocytes, the cells that produce skin pigment |
| How common is it? | Most common type of skin cancer; accounts for about 80% of skin cancers | Accounts for about 15% of skin cancers | Less common than BCC and SCC |
| How does it typically behave? | Usually slow-growing, but can invade and destroy nearby tissue | Generally grows more quickly and can cause greater local destruction than BCC | Can spread beyond the skin to other parts of the body |
| Can it spread | Has very little ability to spread to other parts of the body, but can be locally invasive | Can spread to lymph nodes or other parts of the body, although it usually remains in the skin | The risk of spread depends on the stage and characteristics of the melanoma |
| How is it treated? | Treatment may include surgical removal, Mohs surgery, destruction, topical treatments, radiation, or other approaches depending on the cancer | Treatment may include surgical removal, Mohs surgery, destruction, topical treatments, radiation, or other approaches depending on the cancer | Surgical removal is the main treatment; additional procedures or treatments may be recommended depending on the melanoma |
| Why does early detection matter? | Early treatment can help prevent the cancer from invading nearby structures | Early treatment can reduce the risk of local destruction or spread | Early diagnosis and treatment are important because prognosis depends in part on the stage and depth of the melanoma |
What Does Skin Cancer Look Like?
Skin cancer often occurs on areas of the skin that are frequently exposed to the sun, but it can also occur on areas that do not normally get exposed to sunlight.
How can you tell if a spot is skin cancer? Lesions look different depending on the type you have.
A sudden change in your skin—such as a new growth or evolution in an existing mole—is a common sign of cancer. Some of the typical symptoms are a new mole, changes to the size, shape, and color of a mole, a pearly or waxy bump on the face or head area, or scar-like areas on the skin.
What Are the Risk Factors for Skin Cancer?
Although anyone can get skin cancer, there are certain groups that are more susceptible to the disease. Your risk will be higher if you spend a lot of time in the sun, get sunburned easily or have a history of sunburns, live in a sunny or high-altitude climate, have light-colored eyes, hair, and skin, have freckled skin, have a large number of moles or irregularly shaped moles, have a family history of skin cancer, or are taking medications that suppress or weaken your immune system.
Skin Cancer Prevention and Detection: What Can You Do to Reduce Your Risk of Skin Cancer?
Are there ways to prevent skin cancer? Regular sun protection can decrease your chances of developing future cancers. The following steps should be taken for sun protection. They are listed in order of importance, but should be used together whenever possible:
- Do not intentionally expose your skin to natural or artificial sunlight.
- Avoid sun exposure when possible, especially in the middle part of the day, when the sun is most directly overhead.
- Protect your skin from the sun with a physical barrier. Wear a hat with a broad brim, sunglasses, a long-sleeved shirt, and pants when outdoors.
- Apply a broad-spectrum sunscreen with an SPF of 30 or higher to all skin surfaces that you cannot cover with clothes.
A patient’s long-term outcome for skin cancer depends on a range of factors, including the stage at which the cancer is discovered. That’s why we recommend prevention first and foremost, as well as routine skin checks in order to spot and examine suspicious moles and lesions as early as possible.
What Should You Do If You Have Been Diagnosed with Skin Cancer?
What happens if you are diagnosed with skin cancer? What happens after a positive skin cancer biopsy? The first step is to get treatment for the skin cancer. After this is completed, you should schedule regular follow-up exams with your dermatologist, who will inspect the area where the skin cancer was treated to make sure the malignant cells are not growing back.
The dermatologist will also check your skin for new skin cancers in other areas.
You should also examine your own skin thoroughly each month. Use a well-lighted room and the combination of a full-length mirror and a handheld mirror to check all of the areas that are hard to see. A spouse, parent, or friend can also help you. Notify us of any new growths, any spots that are changing, and any spots that “look funny.” Also pay attention to any spot that bleeds for no good reason or gets a scab that won’t heal. Most skin cancers are discovered by a patient or spouse and then brought to the attention of a doctor. Carefully examining your own skin is the best defense against a future skin cancer.
Once you have been diagnosed with BCC or SCC, you have a 50 percent chance of having another skin cancer within the next five years. Once you have been diagnosed with melanoma, you are in the highest risk group for developing a new melanoma. You should have a full skin exam by a dermatologist two to four times a year for the first five years after the melanoma has been diagnosed, and then at least once a year for the rest of your life.
If you have had melanoma, you need to let your primary care doctor know. You also need to let your doctor know if you develop any health changes, such as unintentional weight loss, severe headache, weakness, and jaundice. Other health care providers who should be notified of your history of melanoma include your dentist, your ophthalmologist, and your gynecologist.
You should notify all of your first-degree relatives—your parents, siblings, and children—that you have had a melanoma, as this skin cancer tends to run in families. All of your first-degree relatives should have a full skin exam by a dermatologist at least once a year.
Contact Us Today
Request your consultation with Dermatology Group of Arkansas to discuss skin cancer diagnosis and treatment in Little Rock and throughout Central Arkansas. Call us at the Dermatology Group of Arkansas at 501-227-8422 or submit a contact form to schedule a consultation.
How is Skin Cancer Treated?
A skin cancer diagnosis can feel overwhelming, but working with an experienced dermatology team can help patients understand their diagnosis and treatment options. At Dermatology Group of Arkansas, skin cancer treatment is based on the type, location, size, and characteristics of the skin cancer.
BCC and SCC Treatment
The first step is usually a biopsy of a suspicious lesion. A pathologist examines the tissue under a microscope to confirm whether it is basal cell carcinoma (BCC), squamous cell carcinoma (SCC), or another condition. Once the diagnosis is confirmed, the dermatologist can recommend an appropriate treatment plan.
Treatment options for BCC and SCC may include:
- Surgical excision
- Mohs micrographic surgery
- Curettage and electrodesiccation
- Cryosurgery
- Topical medications for selected cancers
- Radiation therapy in certain cases
The appropriate treatment depends on the individual cancer. Some patients may require a combination of treatments.
Melanoma Treatment
Surgery is the primary treatment for localized melanoma. The melanoma is removed along with a margin of surrounding normal skin, with the recommended margin based on the tumor’s characteristics and thickness.
For some melanomas, a sentinel lymph node biopsy may also be recommended to determine whether cancer cells have spread to nearby lymph nodes. The decision is based on factors such as Breslow thickness, ulceration, and other features of the tumor rather than a single 1 mm cutoff.
Patients with melanoma that has spread beyond the original tumor may also have additional treatment options, including immunotherapy or targeted therapy, depending on the stage and characteristics of the cancer.
Personalized Skin Cancer Care
No single treatment is appropriate for every skin cancer diagnosis. Dermatology Group of Arkansas evaluates each patient’s cancer and recommends treatment based on the specific diagnosis, tumor characteristics, and other individual factors.
Meet Your Doctors





Meet Your Doctors


Meet Your Doctors







What Is a Sentinel Node Biopsy?
A sentinel lymph node biopsy (SLNB) is a surgical procedure that may be recommended for some patients with melanoma to determine whether cancer cells have spread to nearby lymph nodes. The procedure helps stage melanoma by identifying and examining the lymph node or nodes most likely to contain cancer cells if the melanoma has spread beyond the original skin lesion.
How Sentinel Lymph Node Biopsy Works
A sentinel lymph node biopsy is typically performed during the same operation as surgical removal of the melanoma. Before the procedure, a radioactive substance and/or blue dye is injected near the melanoma. A specialized device and lymphatic mapping are then used to identify the sentinel lymph node—the first lymph node or nodes to receive drainage from the area around the melanoma. The surgeon removes these lymph nodes, and a pathologist examines them under a microscope for melanoma cells.
A positive sentinel lymph node biopsy means melanoma cells were found in the sampled lymph node and may affect the melanoma’s stage and subsequent treatment plan. A negative biopsy indicates that no melanoma cells were identified in the sentinel lymph nodes examined.
When Is Sentinel Lymph Node Biopsy Recommended?
Whether a sentinel lymph node biopsy is appropriate depends on the melanoma’s Breslow thickness, ulceration, and other features of the tumor. Current guidance generally considers SLNB for melanomas measuring at least 0.8 mm thick when the regional lymph nodes do not show clinical evidence of cancer. For melanomas measuring 0.8 to 1.0 mm, the decision may depend on additional risk factors, including ulceration and other unfavorable features.
For this reason, sentinel lymph node biopsy is not automatically recommended for every melanoma. A dermatologist, surgeon, or melanoma specialist can review the pathology report and other characteristics of the tumor to determine whether lymph node evaluation is appropriate.
What Does Sentinel Lymph Node Biopsy Tell You?
The primary purpose of sentinel lymph node biopsy is to identify whether melanoma has spread to nearby lymph nodes and provide important staging information. Although SLNB can help identify microscopic lymph node involvement and guide subsequent management, it is primarily a staging procedure rather than a treatment that removes all potential melanoma from the body.
If melanoma is found in a sentinel lymph node, additional treatment and monitoring options may be discussed based on the patient’s stage and individual circumstances. Current management may include active surveillance of the remaining lymph nodes and, for some patients, additional systemic treatment rather than automatically removing additional lymph nodes.
Skin Cancer FAQs
What Other Skin Concerns Can Be Treated?
In addition to skin cancer diagnosis and treatment, Dermatology Group of Arkansas provides medical and cosmetic dermatology treatments for a wide range of skin concerns. Medical dermatology services include treatment for psoriasis, rosacea, eczema, and actinic keratosis, among other skin conditions. Our practice also offers cosmetic treatments designed to improve skin tone, texture, and overall appearance, including BOTOX®, hyaluronic acid dermal fillers such as JUVÉDERM®, and biostimulatory injectables such as Sculptra®.
Contact Us Today
Contact Dermatology Group of Arkansas today to learn more about skin cancer screening, diagnosis, and treatment in Little Rock, Arkansas, and the surrounding area. Call 501-227-8422 or fill out a contact form to request a consultation.